Opioid prescribing has declined sharply, but rising pharmacy payments and uncertain recovery outcomes keep treatment quality and claim costs in focus.
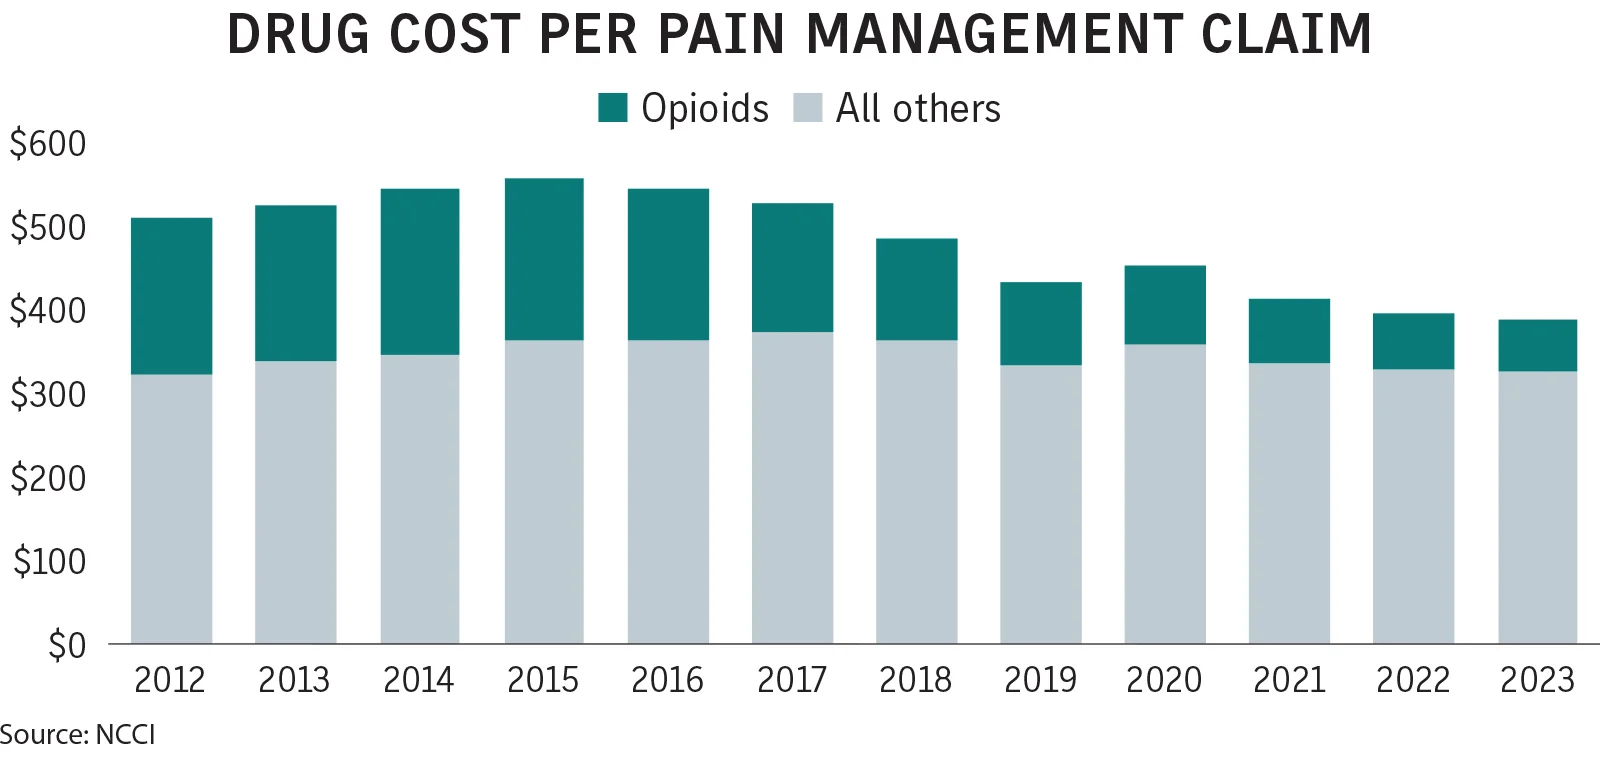
Workers compensation has made clear progress in reducing opioid prescriptions. The less settled question is whether the broader mix of treatments now used helps injured workers recover and return to work while keeping pharmacy spending and other risks in check.
Enlyte’s analysis of retail and mail-order pharmacy transactions billed through its workers compensation pharmacy benefit management program found that opioids made up 19.8% of prescriptions in 2025, down from 30.1% in 2016. Average daily morphine-equivalent dose per opioid prescription fell 35.6% over that period. Those figures show a substantial change in prescribing. They don’t, by themselves, establish how much faster workers recover or whether total claim costs have fallen.
Pain management accounts for about 30% of annual workers compensation medical costs, according to the National Council on Compensation Insurance. “Pain has been and will continue to be a central part of an injured worker’s journey,” said Jon Sinclair, NCCI’s Boca Raton, Florida-based executive director and actuary. Physical therapy and topical medications have become more common, he said, but no single treatment has taken the place of opioids.

Prescribing gains leave an outcomes question
State policies and claims practices have helped reshape opioid use. Sixteen states have drug formularies for injured workers, according to the Workers Compensation Research Institute, and many have prescribing limits or systems to track controlled substances. A study published in Addiction in 2021 found that the number of states with laws limiting opioid prescribing or dispensing rose from 10 in 2016 to 39 by the end of 2019.
The Centers for Disease Control and Prevention’s 2016 opioid guideline addressed primary care prescribing for chronic pain, with exceptions for active cancer treatment, palliative care and end-of-life care. Though voluntary, its recommendations influenced policies adopted by governments and payers. The CDC’s 2022 update covered acute, subacute and chronic pain in adult outpatients and cautioned against turning dosage guidance into rigid limits or stopping treatment abruptly.
That distinction matters in claims administration. Dr. Scott Cherry, chief medical officer of Houston-based Axiom Medical, said administrative thresholds can become inflexible coverage decisions when they aren’t applied to a worker’s individual circumstances. At the same time, maintaining controls that have curbed inappropriate prescribing remains important, said Joe Paduda, president of Skaneateles, New York-based CompPharma.
The next measure of progress is functional recovery. Pain management can affect a worker’s ability to return to the job, and that can shape both disability duration and claim costs, said Ramona Tanabe, president and CEO of WCRI. Dr. Cherry said evidence for declining opioid use is stronger than evidence linking that decline to improved return-to-work rates. Employers, he said, should compare disability duration by diagnosis and treatment approach.
“The most important thing is function in each injured employee,” Dr. Cherry said. Michael MacAulay, president of Mount Laurel, New Jersey-based Lodestar Claims & Risk Services, said success increasingly means faster returns to work, lower total claim costs and better worker outcomes. Effective pain management, he said, balances recovery, function and safety.
That balance can involve higher costs early in a claim. Emily Drew, president and CEO of Helmsman Management Services, Liberty Mutual Insurance’s third-party administrator, said physical therapy may cost more upfront than a prescription. But an earlier return to work and fewer indemnity benefit payments can change the total claim result. “You also have to look at something other than pure cost,” she said.
Alternative treatments bring new pharmacy costs
Lower opioid payments haven’t removed pressure from workers compensation pharmacy spending. In most of the 31 states WCRI examined, prescription payments per medical claim increased between the first quarters of 2022 and 2025. Per-claim opioid payments continued to decline in nearly all of those states. The study covered prescriptions filled within three years of injury on claims unrelated to COVID-19.
Dermatological agents represented 23% of prescription payments in the median state in early 2025 and more than 30% in 12 states. In 20 states, physician dispensing and delivery pharmacies accounted for more than 70% of dermatological payments. The shift points to a practical challenge: replacing one category of treatment can move spending into another.
Nikki Wilson, senior director of clinical pharmacy services for Omaha, Nebraska-based Enlyte, said some topical medications are appropriate when evidence supports their use for a worker’s condition. She cautioned against higher-priced products that don’t offer added clinical value, including new strengths of familiar medications such as ibuprofen and gabapentin. “If you’re going to have a new drug, make sure it’s got efficacy,” she said.
Reviewing individual prescriptions isn’t enough if the full medication regimen goes unchecked. Scott Westman, Lodestar’s Jacksonville, Florida-based senior vice president and chief claims officer, said replacing an opioid with separate drugs for pain, muscle spasms, sleep and anxiety can leave a worker managing several prescriptions. Review should account for medications the worker takes outside the claim as well.
Regular contact with workers and prescribers can reveal when a medication is no longer being used or needs reassessment, said Mina Nakhla, assistant vice president of pharmacy and ancillary programs for Philadelphia-based Gallagher Bassett. Long-term use of other drug classes also calls for periodic review.
Coordinated care can address the whole claim
Coordinating providers may help simplify treatment. For a worker with nerve pain and depression, a pharmacist might discuss with the pain provider and psychiatrist whether one medication could address both conditions, said Andrew Newhouse, director of clinical pharmacy for Rochester, Michigan-based Sedgwick. “We’re treating the workers more as a whole versus just focusing on opioids,” he said.
That broader view includes the psychological effects of an injury. Being unable to work can affect a person’s sense of self-worth, Newhouse said. Jen Laabs, Church Mutual Insurance’s Merrill, Wisconsin-based claim director for workers compensation, said concerns about adding conditions to a claim have sometimes made behavioral and psychological issues uncomfortable for insurers to address. Those concerns shouldn’t keep claims teams from considering factors that influence recovery.
Workers with similar physical injuries may need different support. An underlying health condition or a responsibility such as caring for a disabled child can affect treatment, said Taylor Kostroski, Church Mutual’s senior nurse case manager for workers compensation. She said education and advocacy can help people navigate care and take part in decisions.
Claims administrators are also looking for signs that a claim may lead to prolonged disability, chronic pain or excessive pharmacy use. Predictive models can help flag cases for earlier attention, MacAulay said. At Helmsman, Drew said, the tools give adjusters managing more than 100 files information that can prompt a consultation or connect a worker with resources. Westman said the industry needs to act more consistently on the information these models provide.
Support can begin with an early check-in from a supervisor, Dr. Cherry said. That contact can help a worker stay connected to the workplace without asking for medical details. Case managers can help coordinate communication among the worker, employer and treating providers.
Long-term opioid claims need a measured transition
Workers who have taken opioids for years present a different challenge from newly injured workers. Their claims may involve persistent pain, multiple surgeries and medication plans that began before current prescribing controls. Physical dependence can result from long-term opioid use, but dependence alone doesn’t establish addiction or opioid use disorder, according to the CDC.
Some workers on older claims have reduced their doses without stopping treatment completely, Newhouse said. “Overall, we may not be able to get them completely off the opioids, but can we get them to the next lower level if they’re doing better?” he said. For these claims, improved daily function may be a more useful near-term goal than complete discontinuation.
Before changing treatment, providers need to understand what is causing the pain, said Dr. Frank Tomecek, medical director of Tulsa, Oklahoma-based Precision Motion Health and a neurosurgeon. “Pain is not a diagnosis, it’s a symptom,” he said. Persistent symptoms after back surgery, for example, may call for evaluation of an unresolved or new structural problem. Other workers may need chronic pain specialists, physical reconditioning or a combination of care.
A treatment change should be planned and coordinated. Dr. Cherry said ending coverage before another treatment is available can leave a worker without support. The treating provider should direct the plan, while claims staff arrange authorizations and case managers help manage the transition. The CDC’s 2022 guideline advises against abrupt discontinuation or rapid dose reductions except when there is a life-threatening concern. Tapers should reflect the person’s circumstances and can take months or years, with the risks of tapering weighed against the risks of continued treatment.
Age and other health conditions can complicate medication reviews. Workers may also be reluctant to try a new approach after years on a familiar regimen. Nakhla said older claims may need more frequent reviews, nurse involvement and education. Wilson said changing treatment becomes more difficult the longer a worker has used opioids.
The sector’s prescribing data shows that practice has changed. The harder measure is whether each worker is recovering, functioning and returning to work safely as treatment shifts. For long-term claims, that calls for a patient-specific plan, consistent follow-up and a clear view of outcomes beyond the prescription count.
Discussion
Sign in to join the discussion.